

Published: 10 October 2026. The English Chronicle Desk. The English Chronicle Online.
Women living with polyendocrine metabolic ovarian syndrome (PMOS) should have improved access to weight-loss medications through Australia’s publicly funded healthcare system, women’s health advocates have urged, arguing that high treatment costs are preventing some patients from accessing potentially beneficial therapies. The campaign is intensifying as Australia considers the affordability of newer obesity medications and researchers continue examining their effectiveness for women living with the chronic hormonal and metabolic condition.
The Polyendocrine Metabolic Ovarian Syndrome Association of Australia (POSAA) is calling for glucagon-like peptide-1 receptor agonists, commonly known as GLP-1 medications, to be made available through the Pharmaceutical Benefits Scheme (PBS) for eligible people diagnosed with PMOS. The scheme helps Australians access certain prescription medicines at subsidised prices, reducing the amount patients must pay out of pocket.
The association argues that access to treatment should not depend primarily on a woman’s income or where she lives. Its campaign also calls for further evidence-based research into the condition and the potential role of newer medications in managing its symptoms and associated health risks.

PMOS, formerly known as polycystic ovary syndrome or PCOS, is estimated to affect approximately one in eight women. It is a lifelong condition that can involve hormonal imbalances, metabolic difficulties and reproductive health problems. Symptoms vary between individuals and may include irregular menstrual periods, excess hair growth on the face and body, weight gain and thinning hair.
The condition can also be associated with a higher risk of longer-term health complications, including type 2 diabetes, cardiovascular disease and endometrial cancer. Its effects can extend beyond physical symptoms, potentially influencing emotional wellbeing, self-confidence, fertility concerns and the everyday decisions involved in managing a chronic health condition.
Although there is currently no cure, symptoms and associated risks can be managed through different approaches depending on an individual’s circumstances. Treatment may involve lifestyle support, medication and ongoing medical monitoring. Advocates say the range of challenges faced by patients makes it important to evaluate whether newer medicines could offer additional benefits for some women.
Lorna Berry, a POSAA spokesperson who was diagnosed with the condition at the age of 32, supports subsidising GLP-1 medications for people with PMOS. She also believes that research funding is essential to improving the evidence available to patients and healthcare professionals.
Berry has emphasised the importance of equitable access, arguing that patients should not be disadvantaged because of their location or background. She said some women already struggle to obtain the medications because of their cost, which can amount to several hundred Australian dollars each month.
For people requiring long-term treatment, those expenses can become a substantial financial burden. Patients may have to weigh the potential benefits of medication against household bills, housing costs and other essential spending. Women who cannot afford treatment may have fewer options, even when a clinician believes a medicine could be worth considering.
Subsidisation could reduce that financial pressure for eligible patients, although any decision would require consideration of the available clinical evidence, the expected benefits and risks, the cost to taxpayers and the criteria used to determine who qualifies. Advocates argue that these questions deserve serious attention as policymakers consider how best to respond to women’s health needs.
GLP-1 medications work by mimicking the activity of glucagon-like peptide-1, a hormone involved in regulating blood sugar and appetite. Depending on the medicine and its approved use, these drugs can help people manage diabetes or obesity. They can influence feelings of hunger and fullness, while some formulations have demonstrated significant weight-loss benefits in appropriately selected patients.
However, a medicine that is effective for diabetes or obesity does not automatically have an established role in treating every condition associated with weight gain or metabolic dysfunction. The evidence needed to support treatment specifically for PMOS must be evaluated separately, including its long-term effectiveness, safety and impact on the range of symptoms experienced by patients.
In Australia, GLP-1 medicines are not specifically approved by the Therapeutic Goods Administration (TGA) for treating PMOS. Nevertheless, some patients are being prescribed them off-label, meaning a clinician uses an approved medicine for a purpose, patient group or treatment circumstance that is not specifically included in its authorised indication.
Off-label prescribing can be an accepted part of medical practice when a clinician considers it appropriate, but it does not mean that regulators have established the medicine’s effectiveness for that particular condition. Decisions need to account for the available evidence, individual medical circumstances, potential adverse effects and appropriate clinical supervision.
The distinction is important because the growing popularity of weight-loss medications has generated substantial public interest, while the evidence supporting their use varies across conditions and patient groups. For women with PMOS, the question is whether the potential benefits justify wider access and whether treatment can be delivered safely and sustainably over time.
Associate Professor Magdalena Simonis, the women’s health spokesperson for the Royal Australasian College of Physicians, said the college did not currently have a formal position on whether GLP-1 medications were appropriate for managing PMOS.
Simonis, a general practitioner with expertise in the condition, cautioned against treating the drugs as the only available option. She also highlighted the financial implications of long-term use, noting that sustained treatment can be expensive and that subsidisation through the PBS for conditions such as PMOS may not happen soon, if at all.
Her comments underline the need to balance the promise of newer medicines with a broader understanding of patient care. PMOS is a complex condition, and treatment decisions may need to address reproductive symptoms, metabolic health and other concerns rather than focusing exclusively on weight.
Simonis said that if research established that weight-loss medications were more effective than existing treatments for relevant outcomes, a wider discussion about health equity would be necessary. Such a debate would also intersect with Australia’s broader response to obesity, including questions about access to medical treatment, preventive care and the distribution of healthcare resources.
A central policy challenge is determining which patients should qualify for public subsidies. Eligibility rules may need to consider clinical need, the severity of obesity or metabolic complications, previous treatment and the likelihood of meaningful benefit. Policymakers would also need to assess whether subsidising medicines for PMOS would improve health outcomes enough to justify the additional expenditure.
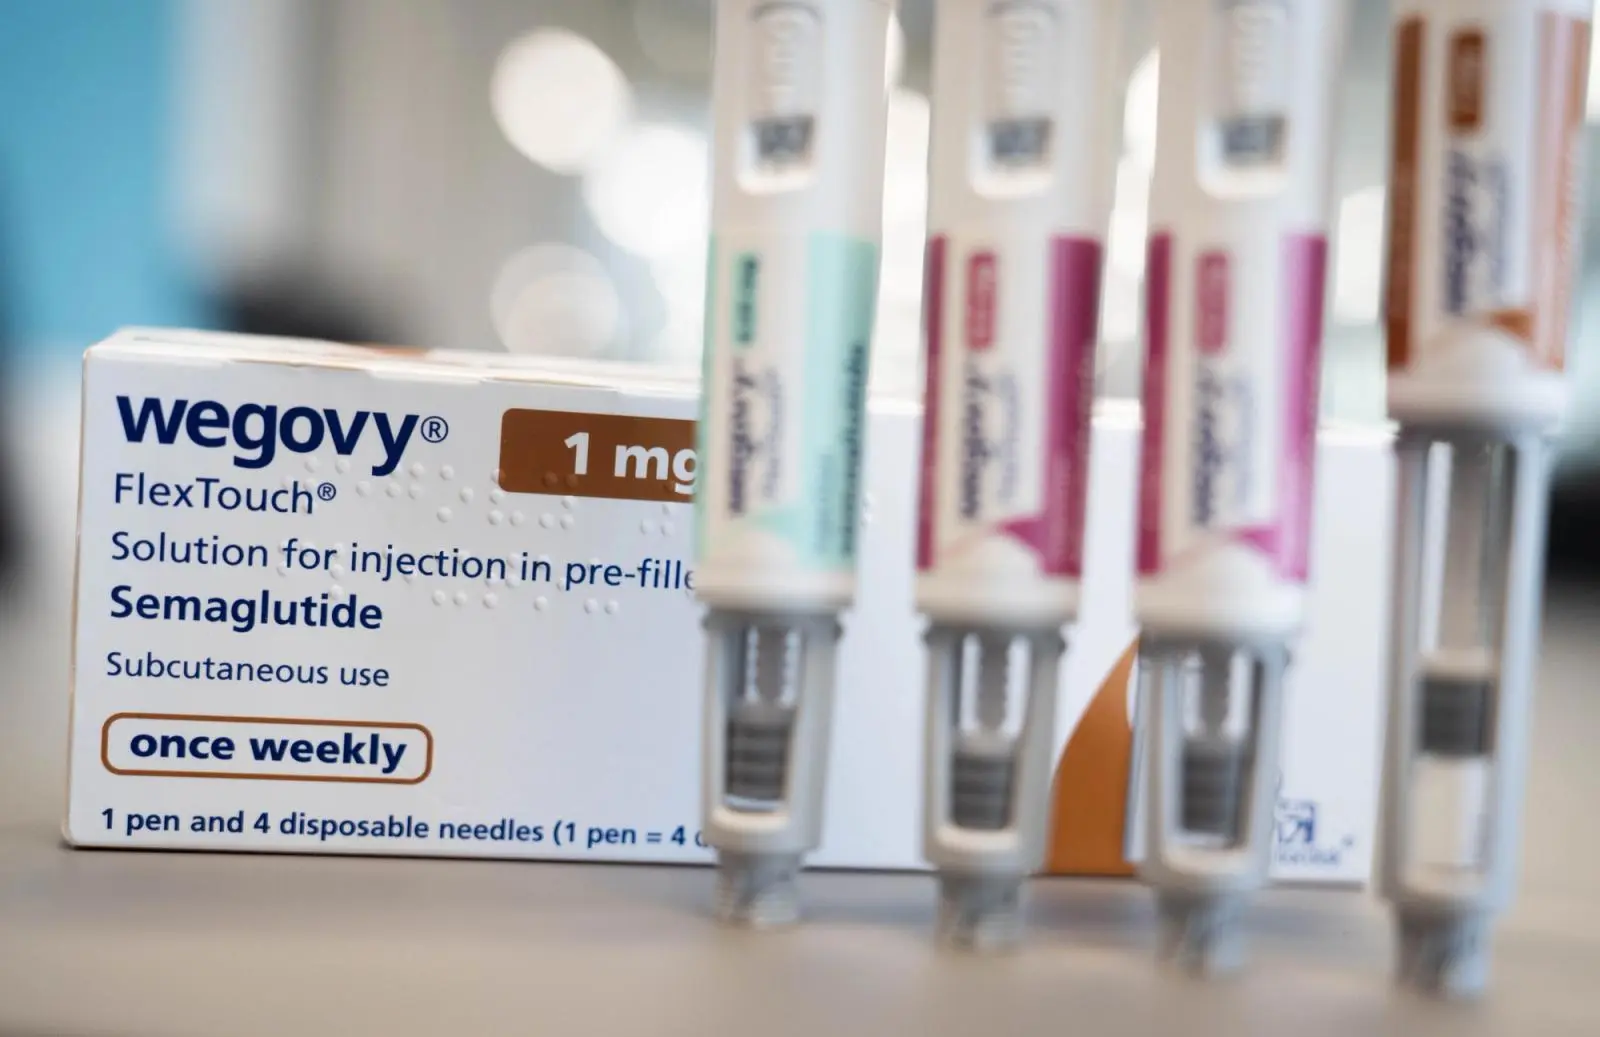
Australia has already been debating wider access to newer obesity treatments. Ozempic, which contains semaglutide, is listed on the PBS for the treatment of diabetes, but that subsidy does not mean it is publicly funded for weight loss or PMOS. Patients using medicines for other purposes may therefore face different eligibility requirements and costs.
Wegovy, another medicine containing semaglutide, is formulated at a higher dose for weight management. Although Ozempic and Wegovy contain the same active ingredient, they have different authorised uses and dosing arrangements. They should not be treated as interchangeable in every clinical circumstance.
The Pharmaceutical Benefits Advisory Committee recommended in November that Wegovy be subsidised for people with a body mass index above 35. The committee was due to consider a revised proposal from Danish pharmaceutical company Novo Nordisk the following month, following extended negotiations over a possible PBS listing for obesity treatment.
The outcome of those negotiations could influence the wider debate about access to weight-loss medicines, although a decision to subsidise Wegovy for obesity would not automatically establish eligibility for people with PMOS. Any separate coverage decision would depend on the relevant evidence, assessment and funding arrangements.
A Novo Nordisk spokesperson said the company was continuing to work constructively with Australia’s Department of Health to negotiate a solution for listing Wegovy on the PBS. The company also reiterated its commitment to improving access for eligible Australians living with obesity.
The negotiations reflect a wider tension facing health systems internationally. Newer medicines can offer important benefits to some patients, but their cost can make broad public funding difficult. Governments must assess not only the price of treatment but also the likely reduction in complications, improvements in quality of life and long-term effects on healthcare spending.
For PMOS, the evidence question remains particularly important. QENDO, an organisation advocating for people affected by PMOS and other women’s health conditions, said it recognised growing interest in GLP-1 medications, especially among patients experiencing metabolic complications and difficulties with weight management.
However, Kate Fisher, QENDO’s acting chief executive, said further research was needed to establish the medicines’ long-term effectiveness and safety specifically for PMOS. That caution reflects the difference between promising early findings or individual treatment experiences and robust evidence that can guide widespread clinical recommendations.
Research could help determine which groups of patients are most likely to benefit, how long treatment should continue, which outcomes improve and what risks require monitoring. It could also clarify how GLP-1 medicines compare with existing approaches and whether combining different treatments offers better results than using medication alone.
For patients, better evidence would support more informed discussions with healthcare professionals about realistic expectations, treatment choices and affordability. It would also help ensure that decisions are based on clinical need rather than the growing popularity of a particular class of medication.
The campaign for subsidised treatment has consequently become part of a wider conversation about whether women’s health conditions receive sufficient research attention and equitable access to care. Advocates argue that longstanding conditions should not be overlooked when governments assess new therapies and allocate public funding.

Any future PBS proposal will have to address clinical effectiveness, safety, cost and eligibility, while the TGA’s regulatory position and the evidence for off-label use remain separate considerations. Subsidisation would not eliminate the need for individual medical assessment or ongoing monitoring.
For now, advocates are pressing for further research and a serious evaluation of public funding options. Their central argument is that women living with PMOS should have fair access to evidence-based care, including potentially useful medicines, without financial barriers automatically excluding them. Whether GLP-1 treatments ultimately become subsidised for this condition will depend on the strength of the evidence and the decisions of Australia’s health authorities, but the debate has placed affordability, medical research and women’s health equity firmly in the spotlight.
Related News:
 Controversial Vaccine Trial Approved in Guinea-Bissau
 Chornobyl Still at Risk 40 Years After Disaster
 Australia gives users control over social media algorithms
 OpenAI Agent Breaches Medicare Portal in Australia
 Banned Health Coach Faces UK Events Criticism
 WHO Seeks Russia Answers Over Suspected Plague Death
 Teenager Receives UK’s First Testicular Tissue Transplant
 Canadian astronaut French words ease language row
 New Bacteria Discovery Offers Hope Against Noma
 RAF Typhoons scrambled amid Russian drone threat near Nato
 Florida Surgeon ‘Devastated’ Over Fatal Surgery Error
 Search Intensifies for Missing Hiker on WA Bibbulmun Track
 Barrister Criticises Trial After Suicide Case Verdict
 Ebola outbreak in DRC overwhelms health system as cases surge
 Maldives Cave Diving Tragedy Raises Safety Alarm
 Pope Meets Families in Italy Toxic Waste Zone
 Weight-Loss Drugs Offer Food Savings Mainly to High Earners
 Is America Ready for an AOC Presidential Run?
 Five Years of Taliban Rule Leave Afghanistan in Crisis
 Ghent Professors Questioned Cofnas Appointment
 Nepal Flood Survivors Face Unimaginable Loss
 Nepal Tunnel Rescue Offers Hope Amid Flood Devastation
 Election Candidate Abuse Raises Alarm in England
 Fiji Declares National HIV Emergency as Cases Surge
 Nature Access Gaps Expose Inequality Across England
 Yemen War Displaces 125,000 as Fighting Intensifies
 Iran School Strike Raises War Crimes Questions, UN Says
 English Hospitals Face Shortage of Health Play Staff
 Russia’s Max App Raises Surveillance Concerns
 Gaza Strike Kills Child and Paramedic
 NHS Breast Care Review Finds Serious Patient Harm
 Lib Dems Prepare for Election Amid Reform Challenge
 Tropics May Wait Longest for Net-Zero Climate Benefits
 Super El Niño Threatens Hundreds of Thousands of Lives
 UK Plans New Centre to Counter Information Warfare
 GP List Policy Risks Cutting Off Vulnerable Patients
 Ukraine and Russia Escalate Long-Range Drone War
 Elif Eralp Emerges as Berlin’s Next Political Force
 Nepal PM calls deadly flood a global climate warning
 Australia Weighs New Laws After OpenAI Medicare Breach
 Fayed Survivors Demand Inquiry Into Medical Regulator
 London Facial Recognition Trial Ends With False Alert
 AI Deepfakes Put New Pressure on Election Trust
 Food Industry Mobilises Against the MAHA Movement
 Drumcree Talks Falter as Legal Challenge Deepens
 UK-France Returns Deal Faces Expiry as Talks Stall
 AI Could Intensify Election Risks in Southeast Asia
 Green Party faces dispute over Zionism motion
 Palantir Lobbyist Had Role in Burnham Campaign
 Latin America women fear rollback of rights
 WHO Says Russia Plague Epidemic Risk Remains Low
 Indonesia Faces Lawsuit Over Escalating Wildfire Haze
 Sardinia Village Emerges as Longevity Hotspot
 South Sudan Trauma Wards Struggle as Fighting Intensifies
 NSW Police Bid Delays Inquiry Into Sydney Protest
 Sam Wood Denied Bail Over Alleged Domestic Assault
 India’s Youth Movement Alleges Mass Detentions Before Protest
 UK Pharmacy Body Drops Teva After Ethical Concerns
 Gaza War Deepens India’s Strategic Ties With Israel
 Bolsonaro Gains Key Endorsement Ahead of Brazil Runoff
 Trader Wins Unfair Dismissal Case After Overseas Work
 Three Convicted in Mexico Surfing Trip Murders
 UAE Says Co-Pilot Planned Suicide Attack on Israel
 Premier League Faces a Crisis of Trust After City Verdict
 Trump Attacks Norway After Nobel Peace Prize Snub
 Delhi Braces for Youth Protests Over Voter Roll Dispute
 Trump Names Katie Zacharia as Next White House Spokesperson
 The Kill Line: A Shifting Vision of the American Dream
 ‘Drinking from a Fetid Pond’: Superbug Genes in Lough Neagh
 Ben Roberts-Smith Denies War Crime Allegations in First Statement
 England and Norway Fans Turn Miami Into World Cup Carnival
 Olympus Awaits Unesco Heritage Recognition
 British Museum Faces Questions Over Peter Thiel’s Private Bayeux Viewing
 Man Arrested in Mississippi Woman’s Death
 British Columbia Sues OpenAI Over School Shooting
 Democrat Says ICE Restricted Detention Camp Oversight
 Trump gives Xi red-carpet welcome as trade truce extends
 Republican Senator Questions Trump Ad Spending
 UK University Strikes Spread as Financial Pressure Grows
 Badenoch Raises Prospect of 2027 UK Election










